How the Brain Learns to Predict Pain (And How We Can Unlearn It)

Photo by Markus Kammermann on Unsplash
How much do you trust what you see, hear, smell, think, and feel?
Many years ago, I would’ve answered, “100%. I trust my senses.” But it turns out, I was wrong. Our brains are remarkable, but they don’t always get things right.
The brain is a prediction machine. It doesn’t “report” reality. It predicts and constructs what we experience.
Take a look at the image below. Does the dark hole seem to expand?
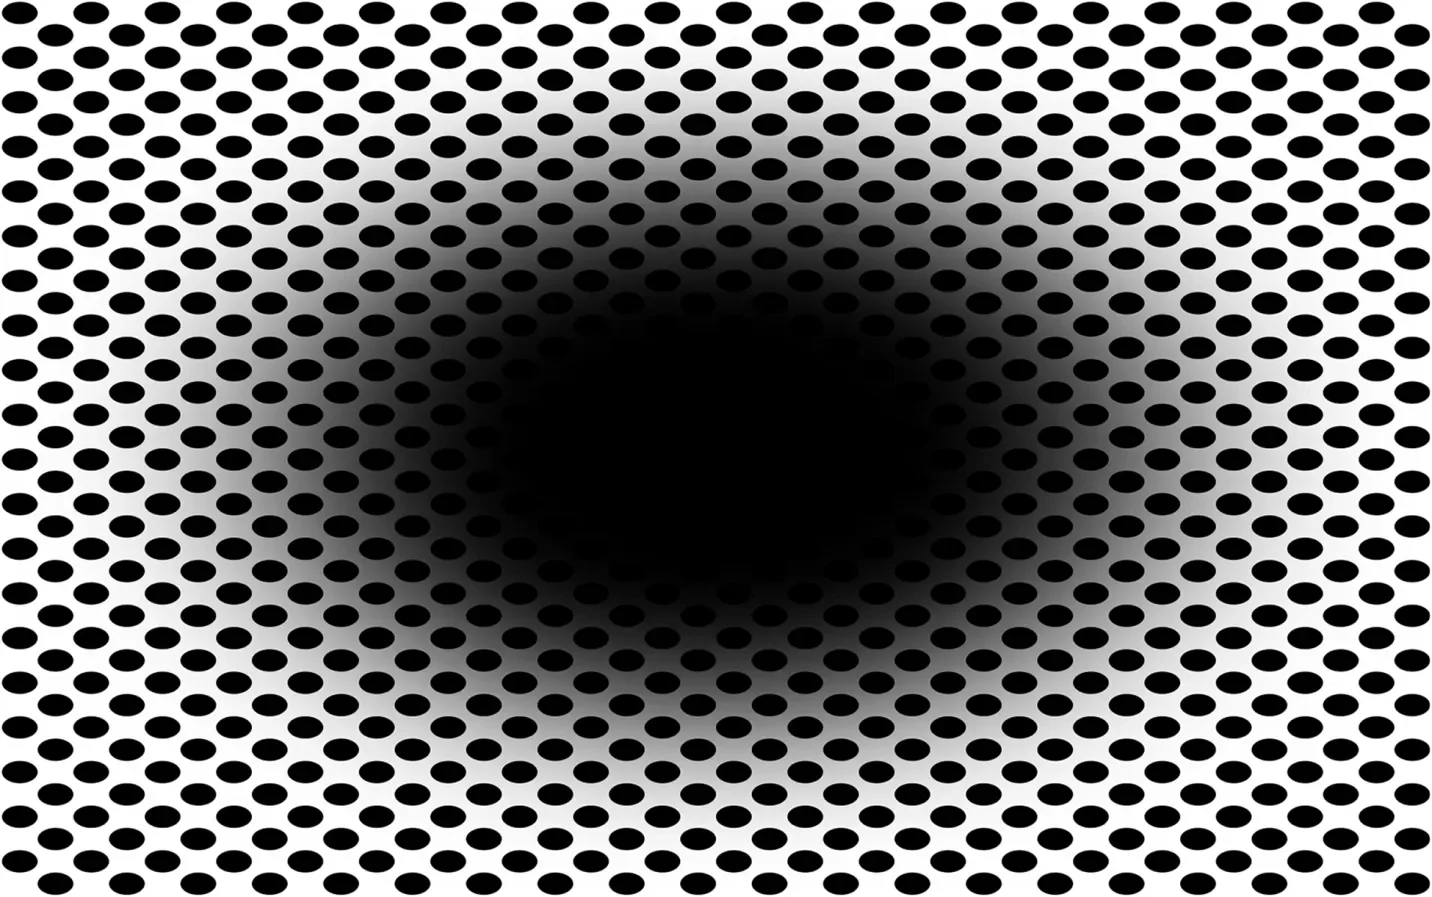
The expanding-hole illusion. Image: Laeng, Nabil, and Kitaoka (2022).
The picture is still. It's not a gif, and nothing is actually moving. Yet, you likely see an expanding dot.
The illusion even produces a physical response from our bodies. Researchers found that participants’ pupils dilated while looking at the dot image. The stronger the perceived expansion, the greater the dilation.
Why does this happen? The researchers suggest that the brain reads the image as moving into darkness. Our pupils respond by letting in more light, even though we haven’t entered a darker space (Laeng et al., 2022).
The brain has generated the perception of movement, and the body responds.
The Predictive-Processing Theory
The signals we receive from our senses don't directly translate to what we see, hear, smell, etc.
We receive signals through our eyes, ears, and other senses, but it is the brain that makes sense of those signals to generate what we experience.
Predictive processing is a theory of how this happens. The brain uses what it has learned to predict what incoming signals mean. Those predictions interact with the signals to shape what we see, hear, and feel (Chen & Wang, 2023).
Here, “prediction” means more than consciously expecting something to happen. In the expanding-hole illusion, you don’t expect to see movement. You just see it. The experience is instant and real.
These predictive processes of the brain usually help us navigate the world quickly and efficiently. But sometimes, what the brain generates doesn’t match what is happening in reality.
How This Relates to Pain
Pain is also an experience shaped by the brain. Whether there is an injury or tissue damage is just one factor that the brain considers in generating a pain experience.
To conclude whether pain is "necessary," our brain takes into account the following among other factors: any danger signals from the body (nociception), the context of the current situation you're in, emotions, and past experiences (Butler & Moseley, 2013). For a further discussion on this topic, you can read Why Pain Doesn't Always Mean Damage.
Predictive processing offers a clue to understanding how pain can occur even without ongoing tissue damage. The brain can learn to predict pain in response to a particular movement, sensation, or even neutral stimuli like certain sounds and smells. That prediction can then contribute to generating pain as the movement or sensation occurs.
If bending has repeatedly hurt in the past, the brain may continue generating pain as you bend, even when the movement no longer poses a risk of damage.
What happens when the brain perceives a car crash that hasn’t actually happened?
In one study, researchers exposed 51 volunteers to a simulated rear-end collision. In reality, the setup, although seemingly real due to sound effect and broken glass, involved so little physical force that the researchers judged it incapable of causing an injury. Nevertheless, about 20% reported symptoms of whiplash within three days. At the four-week follow-up, about 10% reported symptoms, although two of those five participants did not attribute them to the collision (Castro et al., 2001).
When Pain Is the Condition
Medical classification also recognizes that chronic pain isn’t always a symptom of an underlying injury or disease. The World Health Organization’s International Classification of Diseases (ICD-11) distinguishes between chronic primary pain and chronic secondary pain.
In chronic secondary pain, pain is associated with an underlying injury or disease, such as rheumatoid arthritis or cancer. In chronic primary pain, the pain itself is recognized as a condition in its own right, rather than being better explained by another diagnosis. This includes fibromyalgia and many forms of chronic back pain (Treede et al., 2019).
To resolve chronic pain, it may be more important to understand what keeps it going than to investigate what may have started the pain. It is possible that the original injury may no longer be playing a part in generating the current pain.
We Can Unlearn Pain
What would it look like to apply this understanding to recovery and healing from chronic pain?
Years ago, I was struck in the head by another player’s knee while playing soccer. I experienced concussion symptoms for three years. Light and sound became triggers for headaches, overwhelm, and crushing anxiety. I avoided crowded places, movie theatres, screen time, and the list grew over time. I carried a pair of earplugs with me always and stayed in a dark room as much as I could. It was a miserable time.
What I understand differently now is that my brain had learned associations between particular sensations and symptoms. Avoiding those sensations reinforced the message that they were dangerous.
And what does the brain send in response to something it considers dangerous? Pain.
Surprisingly, my recovery didn't come from more rest and continued avoidance. What helped was gradual exposure and teaching my brain that those sensations were safe again. I was giving my brain new, corrective experiences, teaching it that it was now safe for me to do things like watching movies and being in a brightly lit room.
Those activities could aggravate my symptoms, especially early in my recovery. But years later, I understood that ongoing symptoms did not necessarily mean ongoing injury. Even after healing had taken place, my brain could continue responding as though protection was still needed, even when those activities were now safe.
Thankfully, our brains can continue to learn, unlearn, and relearn throughout our lifetime. Neural connections can strengthen or weaken through experience. This capacity for change is called neuroplasticity.
When learned predictions are generating persistent pain, recovery needs to involve changing those predictions. Understanding pain, reducing fear, and safely developing new experiences of movement, sensation, and activity play a key role in that learning.
It often takes patience to change patterns that have developed over years or even decades. But our brains are designed to learn and change. Learning how pain works and putting that understanding into practice gives the brain new experiences to draw from. We can begin to change what it predicts, making it possible to transform our experience of pain.
References
Butler, D. S., & Moseley, G. L. (2013). Explain pain (2nd ed.). Noigroup Publications.
Castro, W. H. M., Meyer, S. J., Becke, M. E. R., Nentwig, C. G., Hein, M. F., Ercan, B. I., Thomann, S., Wessels, U., & Du Chesne, A. E. (2001). No stress—no whiplash? Prevalence of “whiplash” symptoms following exposure to a placebo rear-end collision. International Journal of Legal Medicine, 114(6), 316–322. doi:10.1007/s004140000193.
Chen, Z. S., & Wang, J. (2023). Pain, from perception to action: A computational perspective. iScience, 26(1), 105707. doi:10.1016/j.isci.2022.105707.
Laeng, B., Nabil, S., & Kitaoka, A. (2022). The eye pupil adjusts to illusorily expanding holes. Frontiers in Human Neuroscience, 16, 877249. doi:10.3389/fnhum.2022.877249.
Treede, R.-D., Rief, W., Barke, A., et al. (2019). Chronic pain as a symptom or a disease: The IASP Classification of Chronic Pain for the International Classification of Diseases (ICD-11). Pain, 160(1), 19–27. doi:10.1097/j.pain.0000000000001384.